Wednesday, August 28, 2013

ER Intern: BushHog vs. Legs

So while everyone in the ER knows that the most dangerous thing you can do with yourself when guns are involved is "mind your own business" because that seems to be the #1 reason how people get shot.... what you didn't know is if you are around.... Mowing your law with an industrial mower, is the worst thing you can do for your feet. This last week we have had 4 catastrophic bushhog accidents.

It appears on the screen as bushhog vs leg catastrophe. There is even a billing code for this because it happens so frequently.  I did happen to get an image of one of the more minor injuries as see here. The coolest part of this particular injury is that I was able to take a video of the posterior tibial pulsating because you don't have to feel for his pulse in this one, you can just watch it! Haha. I was just waiting for orthopedics to come down and ask about his neurovascular status.  This guy was pretty lucky. Wile his skin is gone, his achilles tendon and main artieries are intact. He was also able to walk away from the runaway bushhog with this injury.  The will most likely have to graft some skin to cover this over, but he got away scott-free mostly.

Not everyone was this lucky. One guy was coming in by air, but the paramedics with his wife came about 10 minutes early and handed me a lunch box full of grass and toes still in socks.  When he arrive, he had bilateral (both sides) amputation. It was just ground meat that was oozing blood. He had done something that saved his own life. He'd taken off his belt and put it around one leg, the one with the biggest arterial bleed. Even the surgeons gave him kudos for the ability to recognize he needed to stop the bleeding and having the sense to pull the belt TIGHT enough to actually stop the bleeding.  He saved his own life. :) smart guy.  Well minus the drinking and mowing lawn combination.


Here is a guy I saw 24hours after the ATV vs. parked truck event. He reall messed up his girlfriend who had come in the previous night, but this was how his arm looked. He was just walking around with that open and moving it etc etc.... kinda crazy.   We just sewed that sucker up and let him go on his way...


Monday, August 26, 2013

ER Intern: Rashes....

So here are a few crazy cases that should get mentioned. The first may not sound all that cool, but it was my first diagnosis without the help of anyone. And of all things it was hematology. Who would have guessed??

So 16yo kid comes in and presents with "rash" now you know to be suspicious of easy cases in this ER so I'm going in pretty suspicious already.  As you can see from the pictures this is not just a rash, its petechiae, largish all over his body. Petechiae are small bruises under the skin from burst capillaries. And they are all over his
body.  For some freak flash of awesome, the first question I asked after looking at this is are they in your mouth? And yes, yes they are. Along with his bleeding gums.  And I knew, this is ITP (idiopathic thrombocytopenic purpura).  And yes, low and behold his platelets came back at 3. Yep a big ol' 3. So workup for this is to start high dose steriods and call the hematology doctors at 4am because this is legit. And when I said, platelets of 3 - they came right in. :)

Kinda neat.  Lets see another cool case I got was someone in legit SVT with a HR of 290s, sweaty and diaphoretic not responding to adenosine x 3 doses -- so I got to push the shock button. Popped him right out of it... although the guy levitated off the table and screamed "SHIIT" that rang through the whole ER. hahaha. Good thing I gave him drugs so he won't remember how much that hurt. This is the picture of the monitor! Its real.... all the board questions we've been studying are REAL.....


Hm... Another case that was also kind of a mystery case. A transfer from an outside hospital. A guy who had a syncopal or seizure event and came in with a myriad of questionable physical findings. He also had a petechial rash only on his chest and armpits with a purple tongue that was large and

swollen. He was on lisinopril for about 1 year and many were worried he had angioedema. He also had some swelling of the sublingual tissue under the tongue which was different. He was transferred because they were worried about his airway.  You can see that the purple bruising is only on the lateral aspect of his tongue, which gave me a clue as to the fact he'd probably had a seizure earlier that night. I also brainstormed that the petechial rash was most likely from apnea during his seizure that popped the capillaries in his chest. This is often a first sign of cause of death on cadavers in the morgue. My pathology teacher would be so proud of me! So we admitted him, but I didn't give him any angioedema medications because he bit his tongue so hard its probably swollen with all the blood. BAM! I was proud to have sorted this out.

Friday, August 16, 2013

ER Intern: ER Rotator Month-- Incidental Findings

So something I have been learning a whole lot about that seems to be a troublesome topic for many a new doctors, especially in the ER -- is what to do with indicidental findings.  How far do you go into a workup for something that the patient did not come in complaining about?

There is no awesome straight forward answer because many times patients don't know what is important, especially when they are scared or really sick. Who cares about that cat bite a week ago when the patient has a headache?  WE DO, but the patients don't understand that the bacteria from the cat bite went through their bone and infected not just the bone but their blood stream with is causing them to have a headache and be admitted to the hospital.  It is this simple problem that separates a physician from a medical student or intern. What is really important and to some degree what are the right questions to be asking?  This is the "art" of medicine you keep hearing so much about.

Its also something I keep running into as a new physician that makes me look around helplessly. These are things that very few studies have been published on and very few discussions in medical school or residency discuss. The problem with these is generally they aren't a big deal and can cloud your judgement with what the patient is complaining about now. But there are always exceptions especially when the incidental finding is sorta a big deal.

Milliary TB
So here are a few random cases to give you an idea.  I had a gentleman come in complaining of leg and arm pain with a small amount of dyspnea. He is very concerned about his pain and he knows he has a kind of arthritis. The man is about 50ish and is very lean and tall (some would say Marfaniod). Despite this joint pain problem, the real reason his doctor sent him to the ER is that his HR is 45 as I am looking at the monitor. He does not have a history of this and he is not a great athlete.  The patient could give a rat's ass about his HR, he just knows that he's a bit dizzy because the pain in his joints gets to him and he wants something for this joint pain. You can't get him off the freakin subject.  So I order up a cardiac workup, trying to figure out what to do with guy and completely frustrated that I can't get him off the topic of his joint pain. I even throw in a little 800 Ibuprofen medication when I put in orders to help him out.  Anyhow, the chest xray comes back and is this.... I know its hard to see but you can see many tiny nodules scattered throughout the lungs in both fields. And I check the radiologists read just to seek their opinion, yep.... Milliary TB. Uh.... talk about a hell of an incidental finding! So what do I do with this guy now? Obviously I can't just let him go home. Still have no idea why his heart rate is in the 40s, but he has no chest pain and is complaining of joint pain. Alright well TB can go into joints, so I do a generalized xray of a few of his extremities and all it shows is some degenerative changes from real arthritis.  So after some discussion with attending, we decided to do a CT scan of chest to confirm this TB and also see if maybe the TB spread to the heart which would cause his low HR. Maybe.... Alright so we're fishing but obviously this guy is a crazy mystery case. So CT comes back clean other than milliary TB in the lungs.  So I admit him and hope that the internal med folks can figure out what the hell....

There was another guy who was rather cachetic looking came in presenting of some headache. He was older and really not talking much to us, he was a transfer case and didn't have any paperwork for us. So when I talked a little about his headache it was like pulling teeth to get him to tell me any
information. But then I did an abdominal exam.... Oh wait sir, how long have these nodules been here? "Oh yeah... i forgot to tell you. I have stage IV liver cancer and am still on chemo. But also I am a full code."  Yeah! sorta a big thing to know! This guy was suddenly a chatterbox. He even asked me for a rice crispy treat, which i eventually caved, as you can see from the picture. Talk about a crazy finding tho! We immediately were able to treat his headache and nausea vomiting better because we knew it was from chemo. Although I felt sad leaving the room knowing that with tumors like that, he probably wasn't going to make it too much longer. :(  Its horrible to see those kinda patients.

Another weird case was someone coming in complaining of abdominal pain. The guy obviously is having a reoccurence of his pancreatitits since his lipase is 1476. But for some weird reason he is also anemic and since I'm learning the computer ordering system I decide to try the order set, which is a series of standard orders for one complaint. (for example there is an order set for pneumonia or chest pain, etc).  I order up his anemia workup because well he's obviously gunna be admitted. About oh I dunno 7 hours later the intern for internal medicine calls my phone and wants to come talk to me. She's all excited and wants to "pick my brain" and i'm like sure.... So she wants to know how I knew to order the malaria test on this guy because it came back positive! Say what?! Apparently, all the internal med people are all real impressed with me now, which is ironic since all i did was use the order set for anemia.  I told her I didn't think of it and it wasn't my genius. But moral of the story is... USE ORDER SETS. People will think you're smart.

On another randomly intriguing topic. There was a study recently published that we chatted about in conference the other day. It was on "gestalt" this magical ability of a doctor to have a gut feeling about if a pt is sick or really what their diagnosis is. Its what makes doctors keep ordering tests when all the usual tests are negative.  I guess a study actually looked at the accuracy of gestalt in the ER about PEs.  And Interns have a gestalt accuracy of pt having a PE about 71% and Attendings have about 78% accuracy.  I find this interesting and also weird that somebody actually studied this....
now I must acquire another 7% gestalt.... which scares me because it must be one heck of a big 7%.

Tuesday, August 6, 2013

ER Residency: ER "rotator" month

So I'm starting out in the ER. Its a little bit of pressure because I want to be good at everything, and I'm obviously not. That said its only a "rotator" month. So here, they halve the ER and it has 1 upper level and 1 lower level ER intern in each section. The residents who are NOT ER (from psych, internal medicine, OB GYN, etc) are added to one of the halves but are expected to do less. By that I mean carry fewer patients, go slower, and generally ask more questions. They also get reduced hours (they don't work the full 12 hour shifts) and they also only have 16 shifts a month instead of our usual 18.

So as ER interns our first month in the ER (mine just happens to be the first month) we are "rotators" so we can get used to the flow of the ER.  However, we are still on 12 hour shifts and we are still expected to carry more patients than the rotators... about 4 patients at a time.  So we are called "super rotators".... this is all very complicated I know.

Anyhow. My first 4 shifts (all that i've done so far) was a crazy cluster. Its like every patient who comes in here is REALLY REALLY sick.  We are only half thrown the the wolves. We pick up patients and chart and put in our diagnostic orders before

I, as in personally, saw 7 gun shot wounds (GSWs), two of which were life-threatening, bleeding-on the floor, pee-your-pants-cuz-ur-the-doctor-now kinda patients. I had to change my scrub pants twice that night because there was too much blood on my pants to walk around the hospital!! Contrary to popular belief most of the time we leave the bullet in unless its causing problems... I saw 4 septic patients, two of whom I did an internal jugular central line (an IV through the neck which the tube sits in the heart to give certain medications).

I also had a 300lb guy who had headaches, neck pain, and a fever of 103. No nuchal rigidity but luckily I had him walk to the bed from the wheelchair and he was pretty ataxic. So I did my first lumbar puncture. He screamed and legit cried the whole time. It took me about 2 minutes to find the proper spot and I had to get an extra long needle we affectionally call a "harpoon."  But I got it! It was a bloody tap and we ended up diagnosing meningitis.

Another guy came in for a simple headache on and off for the last 2 weeks. He said they were intense pain but lasted only about 5 minutes at a time.  The thing was although his neuro exam was fine, there

was just something off about him. He was having trouble recalling words like "thumb" and seemed to be very distractable, was the text book "inability to concentrate" and so I ordered a CT scan of his head. I had to fight the attending at the time, who was like CT for headaches?? why did you order that? His neuro exam was normal, blah blah blah. Luckily, the scan had already been done by the time he saw I had ordered it.  He had two large masses in his brain, since there was two it was most likely metastasis. And so had to be admitted to try to find the primary cancer. He was close to herniating. Talk about a hell of a first shift!

 They were joking about how I looked like I just got out of high school and I had to tell them he had masses in his brain and likely cancer. It was kinda depressing, yet empowering..... I'm the doctor. And they were looking at me to make the decisions. The attending wasn't there. It was my first solo "bad news" talk.
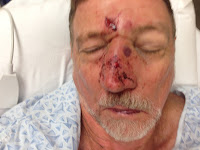
I also had a patient who came in because he "fell out" which is a phrase they use down here to mean passed out. And hit his face on concrete. He had a really intense nasal dislocation and also had
multiple facial fractures below it. It was crazy. So we had to consult opthomology, plastics, and internal medicine to work up the reason for his passing out. Poor guy. He even let me take a picture because he wanted to see what it looked like. :D

I had another patient who I also thought would be a quick case. Guy came in for back pain, he was a young 30 year old. but the more you talk to him the more symptoms he'd come up with. Problems sleeping and his joints ache and blah blah. Turns out he had osteomyelitis of the spine (bone infection) that was so bad, one of his vertebrae was nothing but pus. Even the surgeons said they couldnt' drain it because then there would be nothing left holding up his spine! So much for simple back pain.

Another one that should have been easy (sensing a theme here?) was cough. Turns out that he coughs while i'm in the room. Didn't sound so bad but there was a bit of blood on the tissue paper. It was hard not to notice. So did just a regular Chest xray.... Then I had to do a CT of chest. Its the biggest cavity of Tuberculosis I have ever seen! Ridiculous! Guess I've officially been exposed to tuberculosis (TB) again!!

I also had to run out to the parking lot twice because I almost delivered a baby there. Too bad the baby was too fast :) Delivered itself. Would have been a great story....


Wednesday, July 17, 2013

ER Residency: Honeymoon phase

I'm BACK! and kickin'!  I am soooo happy to report that I am no longer in the funk of post-interview, post-graduation.  I needed the break and loved every second that I wasn't studying. And I finally feel like I can breathe again. Although i'm not quite nervous about residency I'm also not dreadding it.

We do orientation this first month while all you suckers get yelled at we are doing simulations, scavenger hunts and being signed off on chest tubes. And as much as I came in skeptical, I like it here. Okay, I maybe LOVE it. You know how you were so excited for college, and super excited and motivated for med school.... well the honeymoon phase of doing what you've finally chosen hits you like a brick.

Maybe its because I don't know any better, but for now: Its BOMB.  Its not perfect, its a pretty dingy old hospital that sounds like there are lots of problems between surgery and er (big surprise).  There are some attending problems but I can forgive it all.

The other ER intern boys... are epically awesome. Its not all about sports like I feared, they instead bonded over making fun of me, which is all in good fun. They make fun of where I'm from and that I'm the "leader" or whatever. Ha! Its like having 8 lewd brothers. I think the key is I join in sometimes on the "that's what she said" jokes and am not easily offended and suddenly its all okay. We have TONS OF FUN. I am friends with them and their wives. I'm a little heartbroken this month will end and we won't all get to hang out as much. Everyone is very smart but more importantly chill, awesome and hysterical. I could go on, but I realize I'm getting rant-y.

So instead a few things for post-graduation facts before I forget.

#1- Medical licenses are a pain in the ass... apply early and immediately.

#2- There is a rumor that you have to get your residency contract read by a lawyer. Some ppl did and some didn't. But you can't actually change it anyway, so just sign it and move on.  (but do read it!)

#3- Consolidate those loans. It takes a few months for that to go through. And although that means you are giving up your grace periods for the loans... if you are aiming for loan forgiveness through public service you gotta make as many payments on them as possible.  I'm doing the whole Pay As You Go during residency. ((edit: if you don't want the PSLF plan then be sure to go ahead an hire a financial planner you trust, we're talking BIG money now kids. We can't make mistakes))

#4- Screw studying before residency. Instead, decorate your new place, go out or plan something for your new interns and make friends. You WON'T have time later.  That social network turned out to be way more important than I thought.

#5- Do something fun.  Get caught up on all your tv shows or movies or hike in Europe, or do whatever! Do something epic. Its your very last months of freedom.  DO NOT WASTE IT.

Monday, April 15, 2013

End Reflections: Things I didn't say


I'm officially done! No more rotations and no more med school. Forever.  It should be more epic feeling that it does right now. Mostly I feel exhausted.  And I don't even really get to relax because I have to finish my thesis, which really puts a damper on finishing. 

I experienced senoritis in high school, some in college, but it was nothing compared to this. NOTHING.  Four board exams and twenty-seven end of chapter exams later..... I honestly experience extreme apathy..... So apathetic actually that I don't even feel like documenting it.

Instead, I will tell you the down and dirty parts of fourth year that I neglected to document because I didn't want it to get around somehow to program directors....

The most stressful part of med school was audition rotations. I know that I wanted ER and all, but I enjoyed those rotations the least-- which I'm still concerned about.  I hated trying to prove myself everyday and feeling like an idiot and constantly being told I was trying too hard but then I was told I wasn't trying hard enough. There was no pleasing them. It wasn't even the academics that were a big deal in auditions-- it was them judging your personality. Everything in chosing a residency is all about your 'fit' with them. Do they want to see you and deal with you for the next several years? They can teach you whatever you need to know, so they want to know how you learn too.
Other people in non-ER also felt this pressure. Several friends of mine going into OB/GYN or even family were judged based on their personality traits being told they were too dark or too bubbly. They had too much apathy.  I was told in a letter of recommendation (not to my face) this phrase:

"Cared for patients with a strong passion. But over-enthusaism and inability to relax made it so we cannot recommend for residency with a strong conscious."

What kinda crock of shit is that? And it wasn't just one audition, another told me I was too apathetic and not caring enough. I had another that told me I was asking too many questions. WTF!  It was all very disheartening and overall I began to wonder if maybe I wasn't fit for ER. My personality was just not good enough, smart enough, fast enough, caring enough, brash enough, or tough enough. I still carry those doubts with me. Its one of the reasons why I was okay with not-matching.

I started realizing that if at the end of the day I hated myself, maybe it wasn't something I should be doing. I also realized that family medicine wasn't something to dump on and that maybe I was kinda good at it. I also thought hey maybe God and the universe is telling me something, so I accepted that I wasn't going to be the ER doctor I thought, and was shocking okay.  Excited even.  And then I got thrown through a loop because I did match.  And now I have to convince myself that this is what I wanted.... and I'm hoping its what I was supposed to do because.... if I'm still miserable in one year, I have every intention of dropping out and trying to get into family med.

There is some point where I can't work this hard for nothing. And hey, if I'm already decent at family med then why not?  I don't wanna work like a dog until i'm 60.  I want to eventually be GOOD at my job. I want to reach a point where I don't have to constantly feel like I don't know what to do. And maybe its a possiblity that I might not be smart enough to do that with ER. And there is no shame in that. I want to have a life outside of medicine where I'm not studying all the time. I want to have a significant life outside of medicine, to the point where I would consider dropping to part time in the future.

I guess I won't know for awhile what to do, and since I'm bound legally to complete the first year of residency I don't really have to decide right now.  I can only hope I'm not the dumbest person in the room and that i'm good at something within ER.

I also feel somewhat uncomfortable since I'm the only girl in my incoming class. And i still feel like ER is a boys club and I will be left out with any social events. Especially since sports is really not my thing and in ER especially, sports is everyone's thing. Maybe I can be friends with other residents in other specialties.


Its also worth mentioning that several of my audition rotations were 'wasted' because i decided after my rotation there that there was no way in HELL i would ever put that site on my list. That was 3 of the 4 rotations i did. And in that way I also wished I had spent more time thinking and looking into where I did my auditions. At least I know now what size hospital I wanted to train at.... I spend a lot of time thinking about if I had done my list differently would I have got a different spot or not matched or what.... Its kinda unfair we never find out where the place ranked us or what other places thought of us.

whelp... graduation is soon and I gotta get going on this stupid thesis.

In the meantime, I plan to continue this blog into residency although the consistency of the posts may or may not be reasonable.  But i will do my best.

Until July....

Tuesday, April 9, 2013

Elective: Prevention, Nutrition, Anesthetics, Wt loss

So this guy has a different look at medicine.

He is a D.O. And he believes that instead of waiting until disease gets to the point of train wreck, we should treat early to prevent. Basically, we wait until a disaster hits and try to fix it and dont understand why patients still feels crappy.

So he uses the idea of balance and whole body wellness to look at the big picture and then the bad stuff tends to get better on its own. So he looks at nutrition using both blood and urine, as well as toxins like mecury and lead, he also does several specific labs for absorption, tests everyone for hormone levels (not just sex hormones, but thyroid, insulin, and neurotransmitters).  He uses these labs and supplements and diet, exercise to balance those who come into his office.

Its been quite an experience, because I've seen him get his patients off their blood pressure meds, their insulin, and lose weight.  I've seen them stop smoking and they ACTUALLY FOLLOW HIS DIRECTIONS.  And i think the key is he charges cash only and waits until they come to him.  So his patients are those who actually want help.

Its been inspiring to see. And having all his patients leave feeling a little better or looking a little better. I'm surprised at how looking better has a huge impact on mental and physical health. Lots of people who other doctors would call coukey or crazy into alternatives, are really looking for science to help with true health.  Many of them are really sick and have been screwed by regular medicine. Others have always been healthy or alternative and want to stay that way.  Its a good reminder.

My time here has been fulfilling. Being in a healthy atmosphere helps me stay health conscious. It helps the staff and even to some extent the patients. Losing weight, everyone having protein shakes and going to the gym, and sharing good tasting but healthy recipes actually works on my health. I've gone to the gym 5x week and felt pretty good about the things i eat and whatnot. Its good to have that reminder and that motivation.

I'm glad to end my med school career with this good reminder to keep my mind open and don't blow them off. Remembering that patient education is still really important, the diagnosis isn't always the finish line, and prevention is really where it needs to be.

I'd love to come back years from now and consider opening up my own clinic like this and help those around me get healthier.